Understanding the Anion Gap?
The anion gap is a calculated value that helps clinicians gauge the balance between positively charged and negatively charged particles in the blood. It is obtained from common electrolytes on a blood chemistry panel, usually including sodium, chloride, and bicarbonate. Because some ions are not directly measured, the anion gap provides a useful view into overall acid-base balance.
In plain terms, the anion gap helps identify whether there may be extra acids in the body or whether something is altering the usual balance between measured ions. That is why it is often used as a diagnostic clue when reviewing serum chemistry results. The anion gap calculator simplifies this process, but it still helps to understand what the numbers mean before you calculate anion gap values.
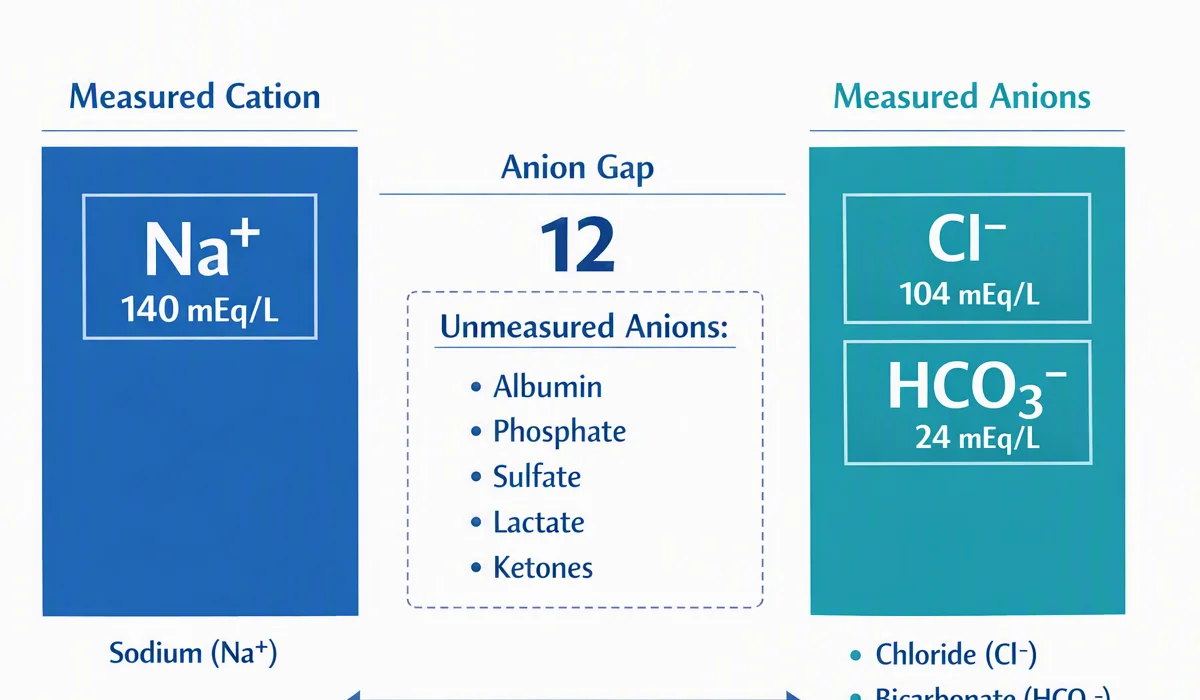
The key idea is that the blood contains both cation and anion components. Sodium is the main measured cation, while chloride and bicarbonate are the main measured anions in the formula. The gap shows the difference between these measured values and the unmeasured substances in the blood, often referred to as unmeasured anions.
When Should You Use an Anion Gap Calculator?
You should apply an anion gap calculator when evaluating an electrolyte panel and you want to review possible metabolic acidosis or a different acid-base disorder. It is especially useful when the clinical interpretation of lab values is not obvious from the individual numbers alone. A calculator can quickly clarify the pattern and support more accurate result interpretation.
This tool is often used when a patient has symptoms or lab findings suggesting a metabolic imbalance, such as low bicarbonate, abnormal chloride, or other changes in the electrolyte values. It can also help interpret a blood chemistry panel when the lab reference values point toward an acid-related problem.
Typical situations where it is useful include:
- Suspected metabolic acidosis Unexplained changes in the electrolyte panel Low bicarbonate with uncertain cause Suspicion for toxin exposure or other causes of acid accumulation Monitoring a known acid-base disorder
The calculator does not substitute for a full clinical assessment, but it does help narrow the differential by showing whether the pattern fits a normal anion gap, high anion gap, or low anion gap picture.
Step-by-Step: How to Operate the Calculator
Using anion gap calculator is easy if you know which lab values to enter. The aim is to enter the right calculator inputs from the patient’s lab report and let the tool handle the calculations. Here is a helpful step-by-step guide.
Step 1: Locate the serum sodium. Look for serum sodium on the lab report. This is the key measured cation used in the formula. Make sure you use the exact value from the same blood draw as the other electrolytes.
Step 2: Locate the serum chloride. Next, locate serum chloride. Chloride is one of the main measured anions and is essential for the calculation. If you see a high chloride result, that may influence the final interpretation.
Step 3: Identify the serum bicarbonate. Identify serum bicarbonate, sometimes labeled CO2 or total CO2 on the lab report. Because bicarbonate is part of the formula, low bicarbonate often signals a possible acid problem and may support suspicion of metabolic acidosis.
Step 4: Put in the values into the calculator. Input the three values exactly as reported. Careful calculator inputs matter because even a small entry mistake can lead to an incorrect result. If the calculator asks whether to use potassium, check whether your clinical setting includes it in the formula; many basic calculators do not.
Step 5: Review the result. The calculator will display the anion gap value. Compare it with the stated reference range or the institution’s lab reference values. The number alone is useful, but it becomes much more meaningful when considered alongside the patient’s acid-base pattern.
Step 6: Interpret the pattern. Decide whether the result suggests a normal anion gap, high anion gap, or low anion gap. This final clinical interpretation step connects the math to the physiology and helps guide next questions and testing.
Tip: Always use results from the same serum chemistry panel. Mixing results from separate moments can distort the calculation and give a false picture of the patient’s state.
How the Equation Operates
The anion gap calculation is built on the balance between measured positive ions and measured anions. In its common form, it is calculated as:
Anion gap = Sodium - (Chloride + Bicarbonate)
It works because sodium is the primary measured cation, while chloride and bicarbonate are the major measured anion components. The result approximates the space left by additional ions that are not directly included in the usual lab panel.
The idea behind the formula is not that something is literally missing, but that the body contains additional charged particles that are not measured routinely. They may include acids or other compounds that influence the anion concentration. When those unmeasured anions increase, the gap often goes up.
The final number should always be interpreted alongside the appropriate reference range. Different laboratories may use somewhat different ranges depending on assay methods and whether potassium is included. That is why the calculator should be considered using the same lab’s values in mind rather than as a absolute absolute.
Understanding the Result
When you know the calculated value, the next step is reading the result. The main categories are normal gap, elevated anion gap, and decreased anion gap. Each can suggest a different type of acid-base disorder or other metabolic issue.
Normal gap: A result inside the expected range usually suggests that the balance between measured cations and anions is intact. However, a normal value does not rule out illness. Some forms of metabolic disturbance can still exist with a normal gap, especially if the bicarbonate is low and chloride is compensating.
High anion gap: A high anion gap often indicates excess acid in the blood or accumulation of undetected anions. This pattern is classically associated with metabolic acid buildup. It is a strong prompt to look for an underlying cause, such as acid buildup or impaired clearance.
Decreased anion gap: A decreased anion gap is less common, but it can occur with low albumin, lab-related issues, or other shifts in measured electrolytes. It is important not to ignore it, because it can reveal a hidden problem or a technical issue in the sample.
In practical medical interpretation, the anion gap is best used as part of a broader picture. Consider the bicarbonate level, the chloride level, the patient’s symptoms, and any other relevant findings on the blood test panel.
Adjusting for Albumin
Albumin strongly affects the anion gap because it is a negatively charged protein in the blood. When albumin is reduced, the measured anion gap may seem lower than expected. This is why albumin correction is often needed for reliable interpretation.
Hypoalbuminemia can obscure a true acid problem. In other words, a patient may have a substantial acid load, but the uncorrected anion gap may look only mildly abnormal or even normal. Using an adjusted anion gap helps compensate for that effect.
The corrected or adjusted anion gap calculates what the value would be if albumin were normal. Different calculators may use slightly different correction methods, but the core principle is the same: lower albumin reduces the apparent gap, so the result should be raised when albumin is reduced.
When using a calculator, check whether it includes an albumin correction field. If it does, enter the measured albumin to get a corrected anion gap. This is especially important in critically ill patients, where low albumin is often seen and can change the interpretation of the lab pattern.
Typical Causes of an Irregular Anion Gap
An abnormal anion gap often indicates a specific category of illness, though it is not definitive by itself. The primary causes are associated with increased acid production, reduced acid removal, or variations in measured proteins and electrolytes.
Elevated anion gap causes commonly include:
- Lactic acidosis, where lactic acid rises due to poor oxygen delivery, shock, or severe illness Ketoacidosis, which can occur in diabetes, starvation, or alcohol-related states Renal failure, where the kidneys cannot clear acids effectively Toxins, including certain ingestions that generate or contain acid-forming substances
These conditions elevate the burden of acids or unmeasured anions, leading to a high anion gap. In many cases, the gap rises alongside a low bicarbonate, which is another sign that the body is neutralizing excess acid.
Decreased anion gap causes are rarer but may include hypoalbuminemia, some forms of lab interference, or marked changes in measured ions. If the gap is unusually low, review the sample and the overall clinical context before drawing conclusions.
Because several different disorders can produce similar numbers, the anion gap should be treated as a diagnostic clue, not a final answer. It helps focus the workup, but it does not reveal the exact diagnosis on its own.
Frequent Errors When Using the Calculator
Even a trustworthy calculator can produce misleading results if the inputs or interpretation are wrong. The most common errors are easy to avoid once you know what to watch for.
Lab error: If the specimen was mishandled or the values do not fit the clinical picture, a lab error should be considered. Checking the sample again or repeating the panel may be necessary before acting on the result.
Unit mismatch: A unit mismatch can cause big problems. Ensure the calculator expects the same units reported by the lab. Entering values in the wrong format can distort the math and lead to a false interpretation.
Missing values: An anion gap depends on complete data. If the report is missing serum sodium, serum chloride, or serum bicarbonate, the calculation will be unreliable. Do not guess; use a complete electrolyte panel.
Interpretation error: A numeric result is only part of the story. A normal anion gap does not always mean “normal,” and a high anion gap should be interpreted in context. The most common interpretation error is treating the number as a diagnosis instead of a clue.
Also remember that albumin changes can alter the apparent value. If albumin is low, failing to use albumin correction may hide a meaningful abnormality. For the best accuracy, always review the full blood chemistry panel and confirm the values before making decisions.
FAQ: Anion Gap Calculator Questions
What numbers do I need to use an anion gap calculator?
Typically, you need serum sodium, serum chloride, and serum bicarbonate. Some calculators also allow albumin so they can provide an adjusted anion gap. Be sure the numbers come from the same blood chemistry panel for accurate clinical use.
What is a normal anion gap?
A typical normal anion gap falls within the lab’s stated reference range. The exact range may vary by laboratory and method, so always follow the value that matches the lab report. A normal result can still warrant further assessment if other findings point to decreased anion gap causes an acid-base problem.
Why do you correct the anion gap for albumin?
You adjust for albumin because low albumin can make the gap seem smaller than it really is. In hypoalbuminemia, the uncorrected value may fail to detect an important problem. Albumin correction helps show the true adjusted anion gap and supports interpretation.
What does a high anion gap mean?
A high anion gap often suggests excess acid or increased unmeasured anions. Common causes include lactic acidosis, ketoacidosis, renal failure, and certain toxins. It is an important clue in evaluating metabolic acidosis and other forms of acid-base disorder.
Can an anion gap calculator diagnose a condition by itself?
No. An anion gap calculator helps with clinical interpretation, but it cannot diagnose a condition on its own. It is one piece of evidence used to interpret lab results alongside symptoms, exam findings, and other tests. The calculator is most useful when combined with full clinical assessment and lab context.